Tretinoin can meaningfully lighten post-inflammatory hyperpigmentation (PIH) and improve some cases of melasma, with the people most likely to benefit being those with acne-related dark marks and those with melanin-rich skin. Early changes often show up around 4 weeks, with clearer fading by 12 weeks and more by 40 weeks. Irritation is common, and tretinoin is not used during pregnancy.
TL;DR:
- In a trial lasting 40 weeks, 58% of patients had lesions rated much lighter, compared with 7% using inactive cream.
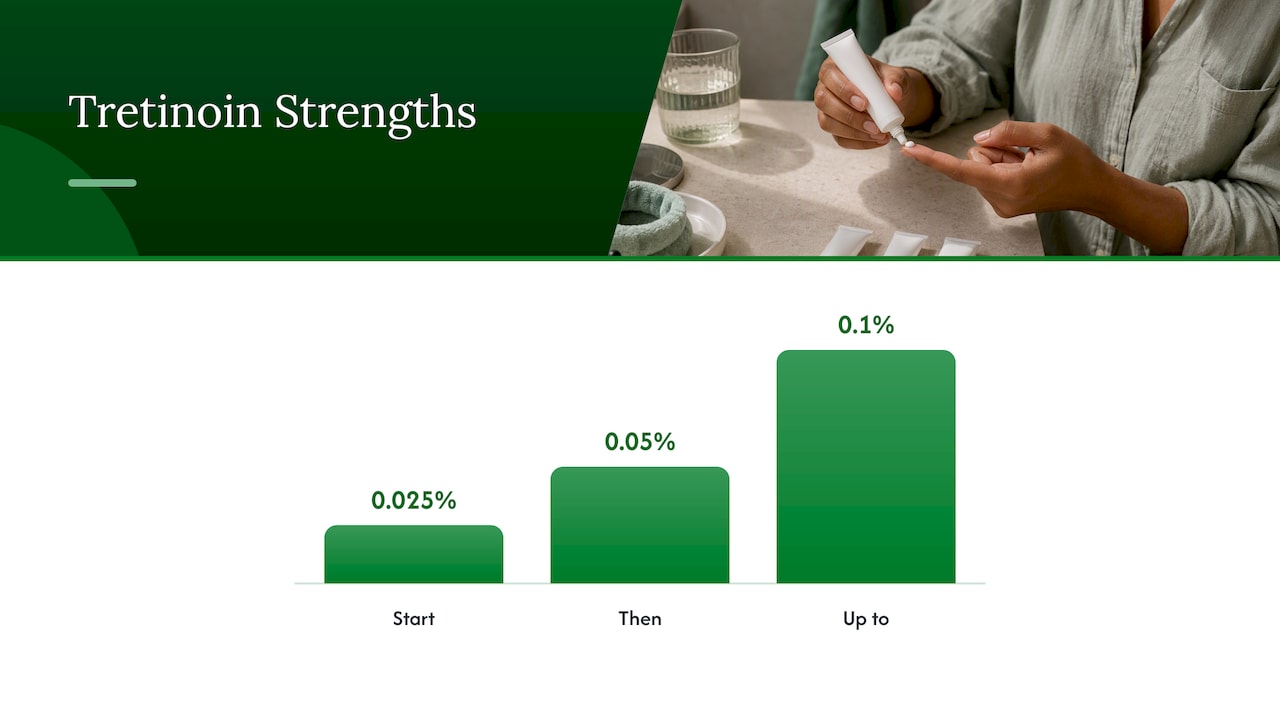
- Clinicians usually start with 0.025% cream, then increase to 0.05% or 0.1% as tolerated; reduce use if redness, stinging, or peeling develops.
- Hydroquinone and azelaic acid target pigment through different pathways; triple combination cream has strongest melasma evidence, but clinicians limit it to short courses with monitoring.
- Daily broad spectrum SPF 30 or higher helps prevent new pigmentation; pause tretinoin before peels or lasers and restart after redness and peeling settle.
- If consistent use produces no visible change after 12 weeks, ask a clinician about adjusting the strength or adding another active ingredient.
Tretinoin is a retinoic acid derivative that speeds up skin cell turnover, which pushes pigmented cells to the surface faster and helps break up uneven melanin deposits sitting in the epidermis. It also calms the inflammation and clears the clogged pores that drive acne in the first place, and since acne flares are what trigger most PIH, reducing breakouts helps prevent new dark marks from forming while existing ones fade.
Formulation affects how well people tolerate treatment, which in turn affects how well it works:
The strongest data point on tretinoin for PIH comes from a 40-week randomized, double-blind trial in patients with darker skin. Using 0.1% tretinoin cream, researchers found clinical improvement in a large share of treated patients compared with vehicle, with colorimetry confirming the lesions moved substantially closer to normal skin tone by the end of the study.
A large share of patients using tretinoin saw their hyperpigmented lesions rated “much lighter” after 40 weeks, compared with a much smaller share using the inactive vehicle cream, and objective skin-tone measurements backed up the visual results.
A few other findings round out the picture:
Hydroquinone works differently from tretinoin: it blocks the enzyme that produces melanin rather than speeding up cell turnover, which is why the two are often paired rather than treated as competitors. Triple-combination cream, which pairs fluocinolone, hydroquinone, and tretinoin, has strong trial support for melasma specifically, though it is meant for short-term, clinician-monitored courses rather than indefinite daily use.
A few comparisons help frame the choice:
Clinicians typically start at a lower concentration, such as 0.025% cream, and titrate up toward 0.05% or 0.1% as tolerability allows, rather than jumping straight to the strongest formulation.
Tretinoin is contraindicated during pregnancy and is generally avoided when actively trying to conceive, in line with standard prescribing guidance for topical retinoids. Daily sunscreen, broad-spectrum SPF 30 or higher, reapplied every two hours during sun exposure, is not optional: tretinoin increases sun sensitivity, and unprotected UV exposure can undo progress by triggering new pigmentation.
Pro Tip: Apply tretinoin to fully dry skin and follow with a fragrance-free moisturizer to cut down on peeling during the first few weeks.
Patience matters more with tretinoin than with almost any other pigment treatment. In the pivotal 40-week trial, researchers noted some improvement as early as week 4, but the gap between tretinoin and vehicle widened substantially by week 40, which is when the largest effects showed up.
By week 40 of continuous use, 58% of tretinoin-treated patients had lesions rated much lighter, versus 7% on vehicle alone, a gap that underscores why sticking with treatment matters more than switching products every few weeks. If there is no visible change after 12 weeks of consistent use, that is a reasonable point to check in with a clinician about adjusting strength or adding a second agent.
Pairing tretinoin with hydroquinone or azelaic acid is a common, evidence-supported strategy, since each targets pigment through a different pathway. Triple-combination cream built around fluocinolone, hydroquinone, and tretinoin has the strongest trial data specifically for melasma, though it is meant for defined courses rather than continuous use.
Getting a tretinoin prescription typically starts with a dermatology evaluation, and we built our online dermatology consultation to handle that step from home. A clinician reviews your skin history, confirms tretinoin is appropriate, and can prescribe it along with guidance on which strength and formulation fits your skin type.
Same-day scheduling is sometimes available, and follow-up messaging with your provider can help adjust frequency or concentration if irritation occurs during the first few weeks. Our guidance on pairing tretinoin with moisturizer is part of that ongoing support, not a one-time instruction sheet.

A prescription strength tretinoin regimen works best when someone is watching for irritation and adjusting the plan as your skin responds, which is exactly what an ongoing telehealth relationship is built for.

Getting started takes a few steps:
If cost or insurance questions are a concern, pricing is clarified before committing to a plan, and follow-up visits are available if your skin needs a different concentration down the line.
Tretinoin works, but it works slowly and only with daily sunscreen. Give it 12 weeks before judging results, and get prescription guidance rather than guessing on strength alone.
— Bryan
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Tretinoin can significantly lighten many hyperpigmented lesions rather than erase them completely. In a 40-week randomized trial, 58% of patients saw their lesions rated much lighter, compared with 7% on an inactive vehicle cream.
Many people notice early changes around 4 weeks, with clearer improvement by 8 to 12 weeks. The largest gains in controlled trial data showed up by week 40 of continuous use, so results build gradually rather than quickly.
Hydroquinone and tretinoin work through different mechanisms, blocking melanin production versus speeding up cell turnover, which is why they are often combined rather than compared head to head. A network meta-analysis of melasma treatments found combination approaches generally outperform either ingredient used alone.
The right starting strength depends on skin sensitivity and is best determined through an online dermatology consultation rather than guesswork.

